

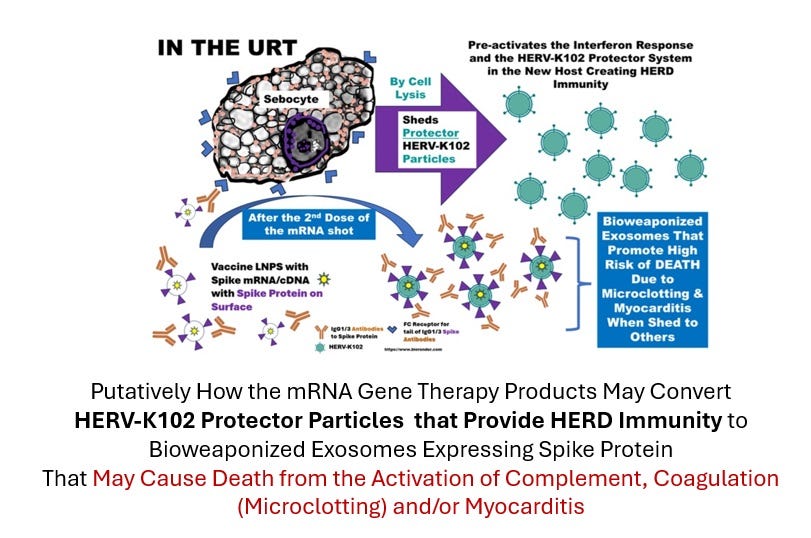
Image 1. Proposed Model for Shedding from the Upper Respiratory Tract (URT) Causing Non-COVID-19 Injuries (including Myocarditis) and DEATHS (a.k.a. bioweaponized HERV-K102)
Shedding (Image 1) only occurs with the Pfizer-BioNTech injection because apparently only this mRNA is significantly contaminated with spike protein. Spike protein allows the targeting of the LNPs to the M1-like foamy macrophages (the sebocytes) in the upper respiratory tract (URT) via the strong induction of spike IgG1/3 antibodies in the URT which mediate entry into the macrophages (sebocytes) via antibody dependent enhancement (ADE) of infection into macrophages. Once inside the sebocytes that are producing high levels of HERV-K102 particles, it is reasonable to assume that 1) high levels of spike protein are produced within the highjacked cells and 2) that both the spike protein and the mRNA/cDNA encoding spike and/or the SV40 cancer causing sequences become incorporated into the HERV-K102 particles. Since this is not self-replicating mRNA/cDNA it means while spike laden HERV-K102 that then becomes covered in spike IgG1/3 antibody commonly happens, only a few of the released HERV-K102 particles would carry the spike and/or SV40 sequences.
At the time of the proposal of the above model [1], there was only evidence that spike protein (actually S2) covered the CD9 exosomes (ie., derived from macrophages, thus, likely HERV-K102 particles) after 14 days following the Pfizer-BioNTech injections in vivo [2], but Bansal et al, did not check for spike or SV40 mRNA/cDNA. The delay to 14 days (the average time it takes for IgG1/3 antibody to spike to be made following the second dose) argues that the spike IgG1/3 were instrumental in the ADE mediated entry of the LNPs into sebocytes.
However until now no one had tested for the existence of spike mRNA in the exosomes (or alternatively had tested but the results were largely negative).
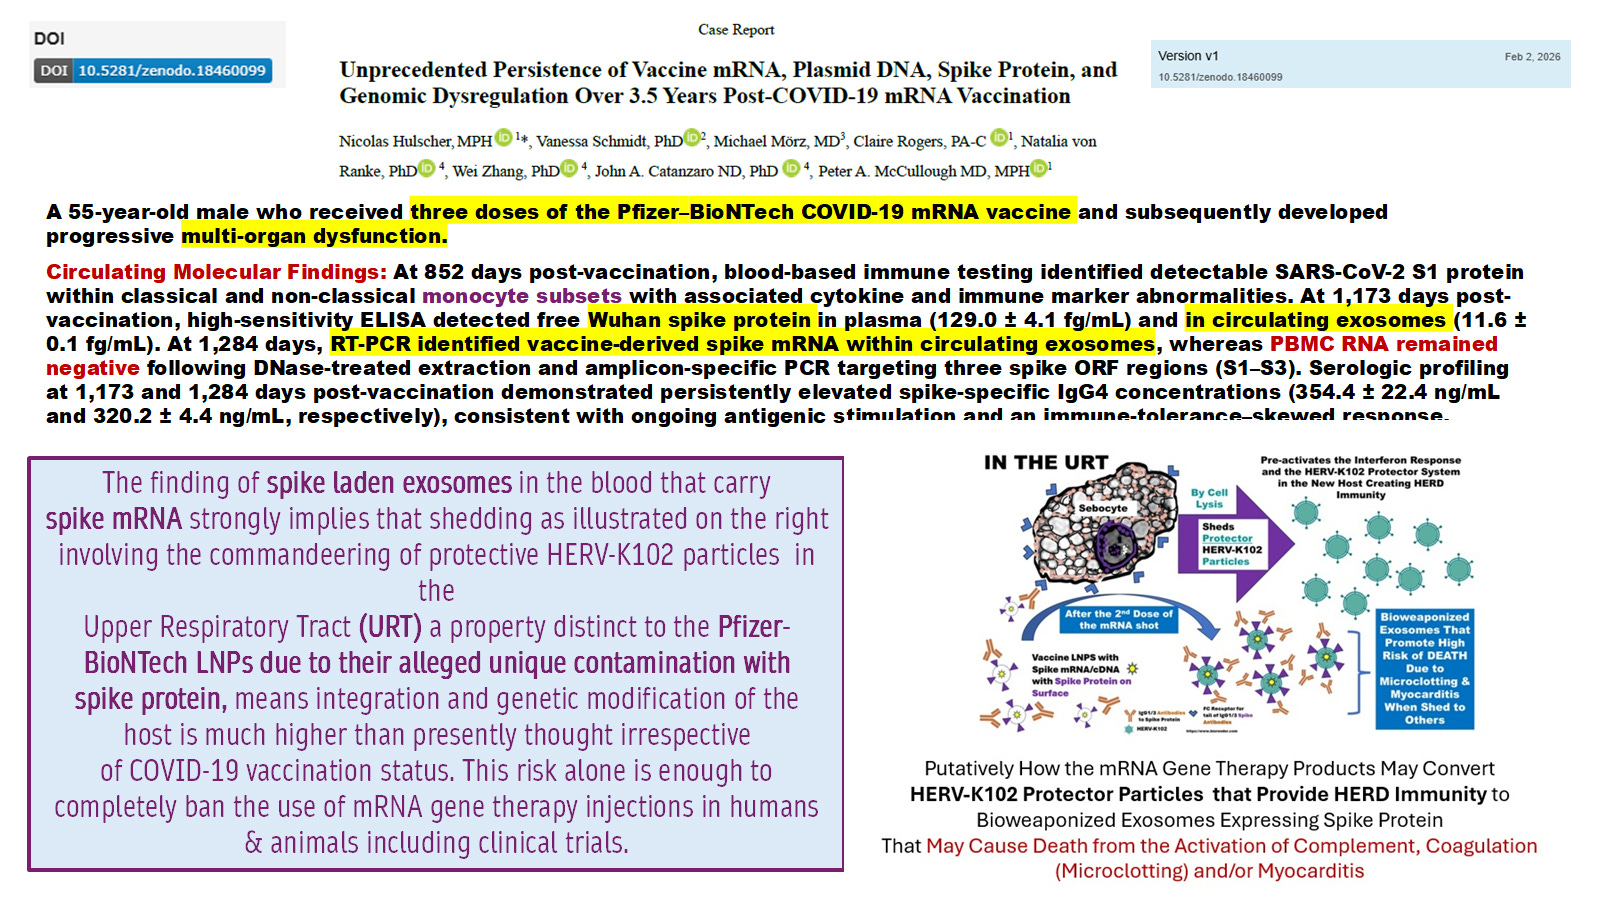
Image 2. A case of likely integration of Pfizer-BioNTech Spike mRNA/cDNA in Macrophages/Sebocytes in an Unknown Location in the Body
As illustrated in Image 2, this person [3] likely has spike mRNA/cDNA integrated in a macrophage/sebocyte cell which produces spike laden exosomes with spike mRNA. I would think this would still be a very rare event, but is the first time it is REPORTED that the exosomes (in this rare case of integration putatively in a macrophage cell type but could also be a cancer myeloid cell-type) carry the mRNA/cDNA encoding the pathological spike protein.
When we also consider that the previous case of integration in vivo although only a 22 base pair segment of spike protein which was remarkably oncogenic [4], it turns out that the integration apparently used the machinery of HERV-K102 (Image 3) which is a non-pathogenic, protector foamy retrovirus of humans [5].
HERV-K102, of the HERV-K HML-2 youngest provirus group integrated in the human genome, is the only KNOWN replication competent virus in the human genome. It is replication competent as demonstrated in vivo in response to viral infections and in vitro [6,7]. As shown in Image 4, HERV-K102 increased integration into genomic DNA (related to high replication activity in vivo) correlated with resistance to HIV-1 acquisition in an HIV-1 Exposed SeroNegative (HESN) cohort [7].
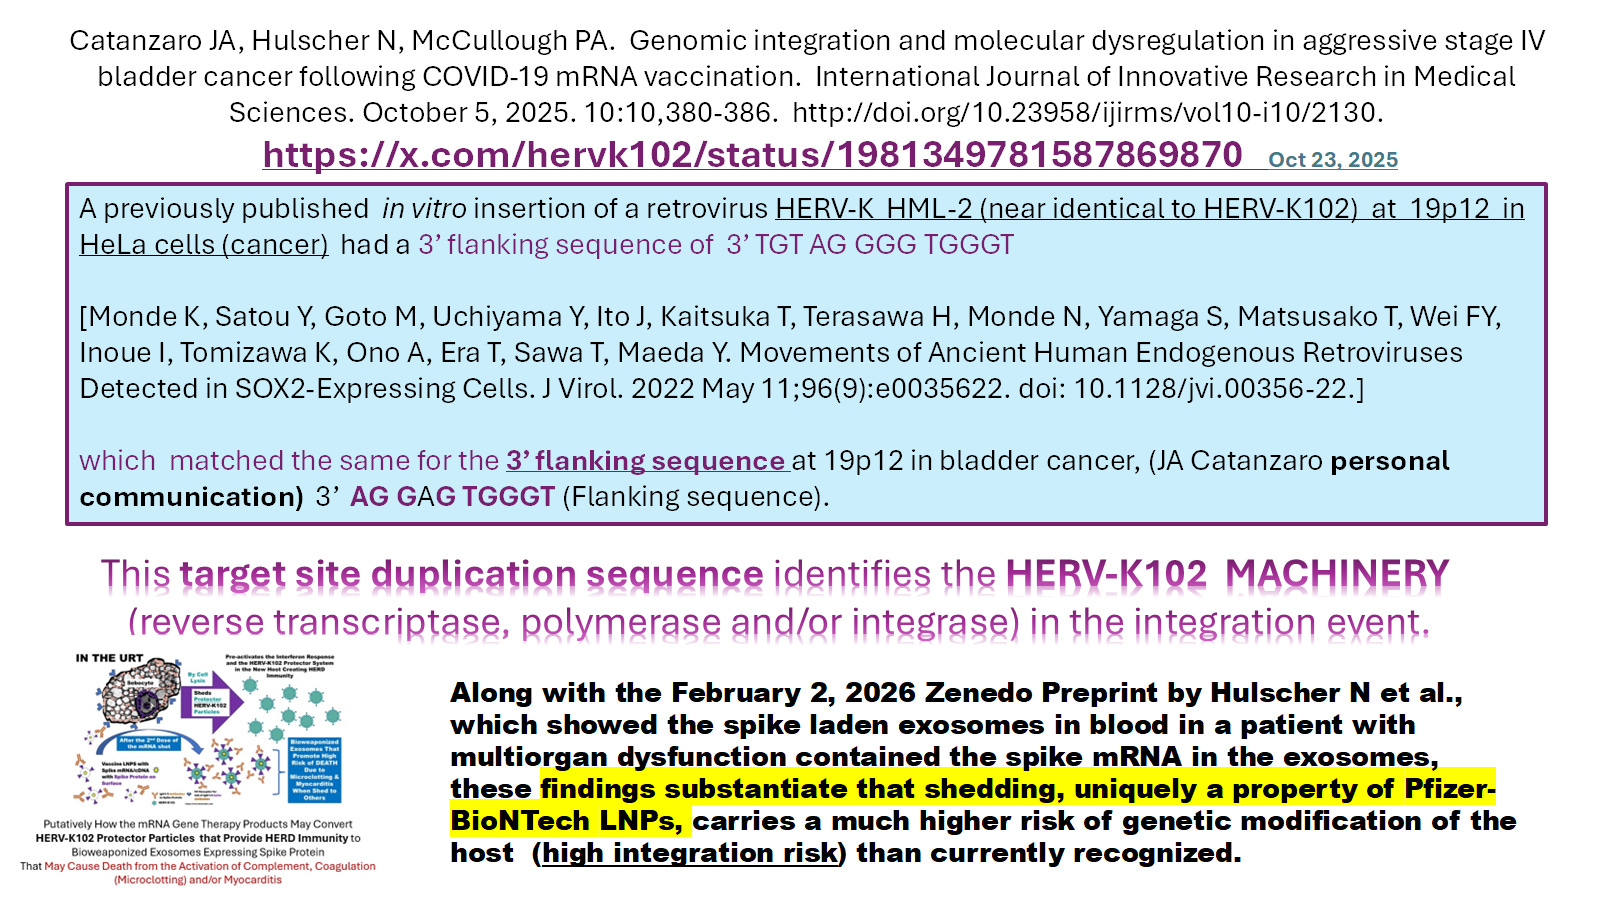
Image 3. The 3’ flanking sequence of the integrated spike segment identifies the HERV-K102 integration machinery in the integration event.
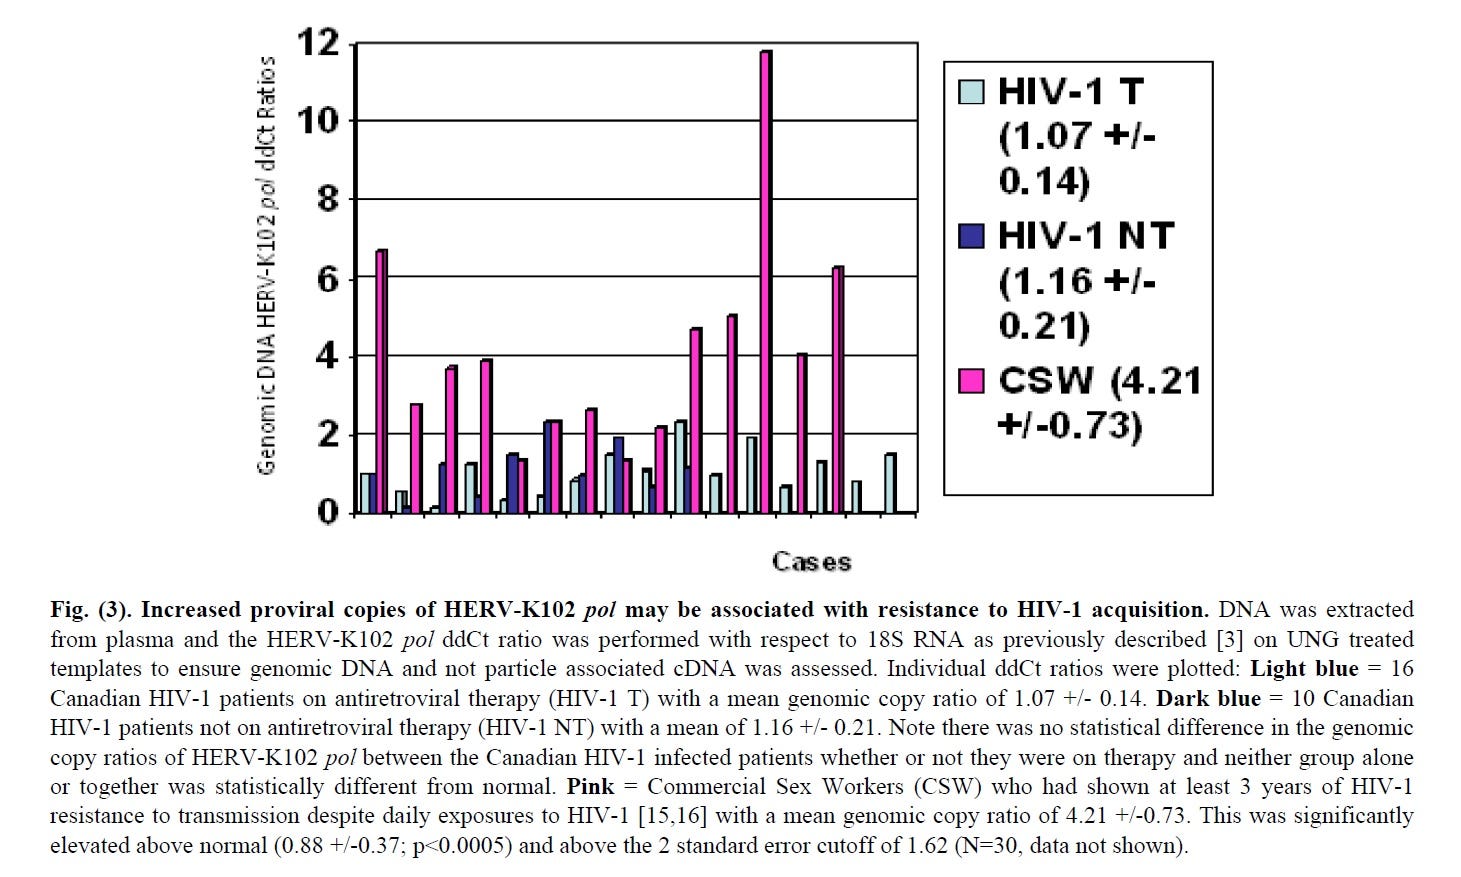
Image 4. Proof that HERV-K102 particles contain functional enzymes that promote integration.
Thus, taken together these result imply that shedding (bioweaponized HERV-K102) unique to Pfizer-BioNTech may rarely contain spike and/or SV40 mRNA/cDNA in direct contact with the HERV-K102 integration machinery, raising the risk of genetic modification of the host that is shed upon.
It should be remembered that according to deaths reported toVAERS, shedding was a common cause of death (Image 5) putatively about 64% of all reported deaths up to January 2, 2026 and reached as high as 92% of all reported deaths shortly following the second dose during the peak “shedding” months.
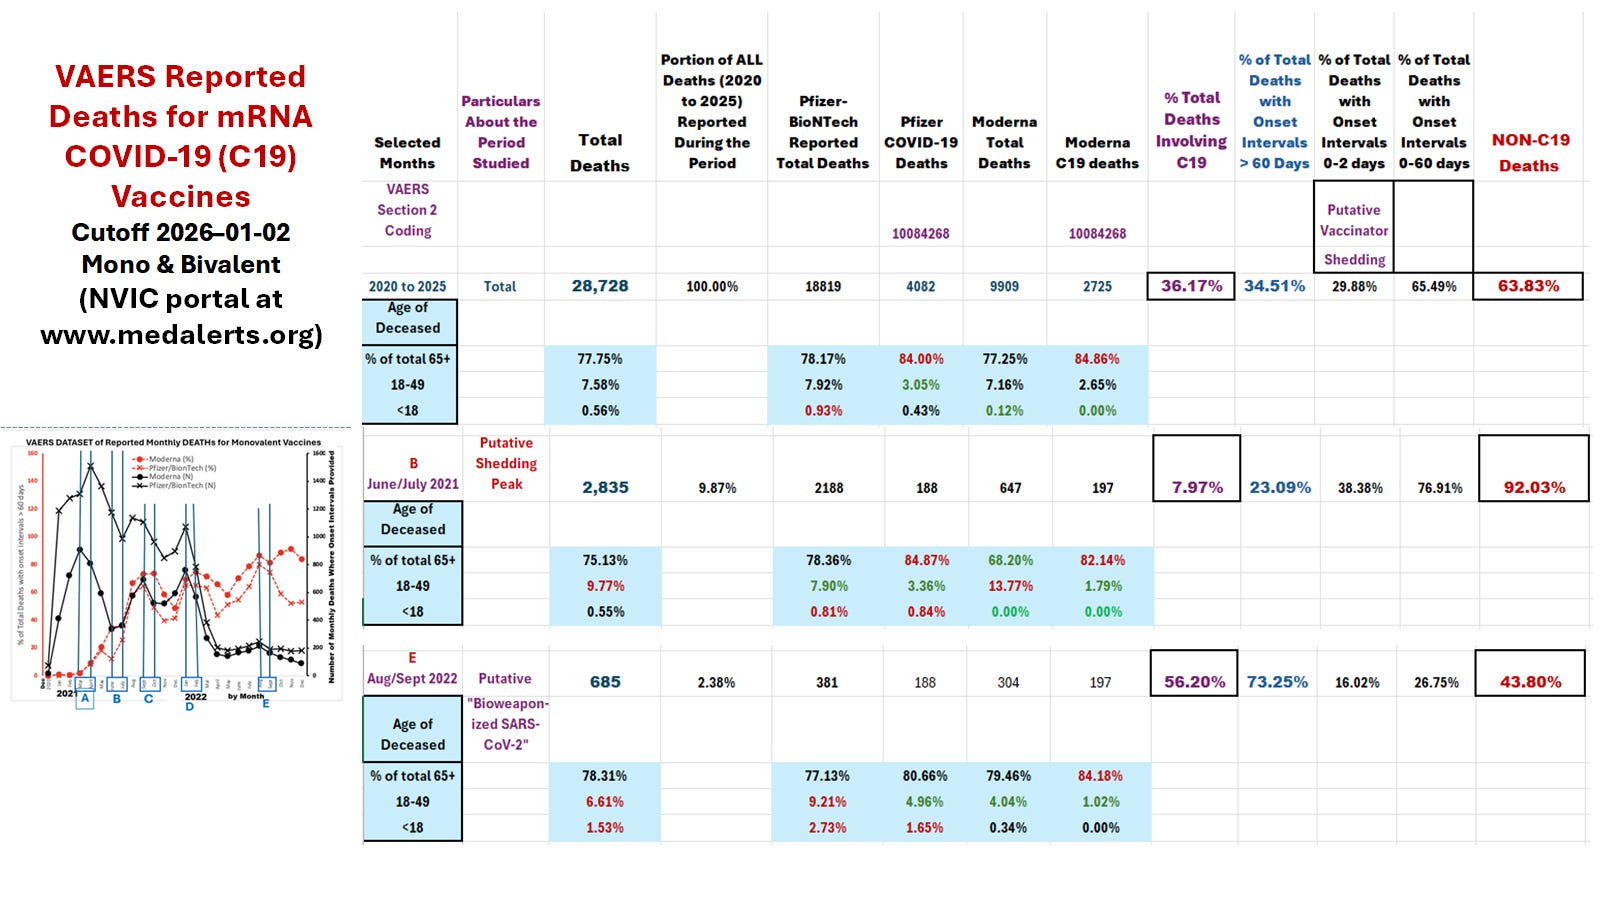
Image 5. Shedding Caused the Majority of Vaccine -Associated Deaths Reported to VAERS up to January 2, 2026.
NB: Deaths within the first 0 to 2 days is thought to relate to shedding by the recently Pfizer-BioNTech immunized vaccinator and is labeled as “Putative Vaccinator Shedding”. Shedding from the vaccinator may have occurred at clinics where the Moderna mRNA gene therapy products were administered. Note that the majority of COVID associated deaths reported to VAERS in the vaccinated (up to about 90%) likely pertained to bioweaponized SARS-CoV-2 (Image 6) [9].
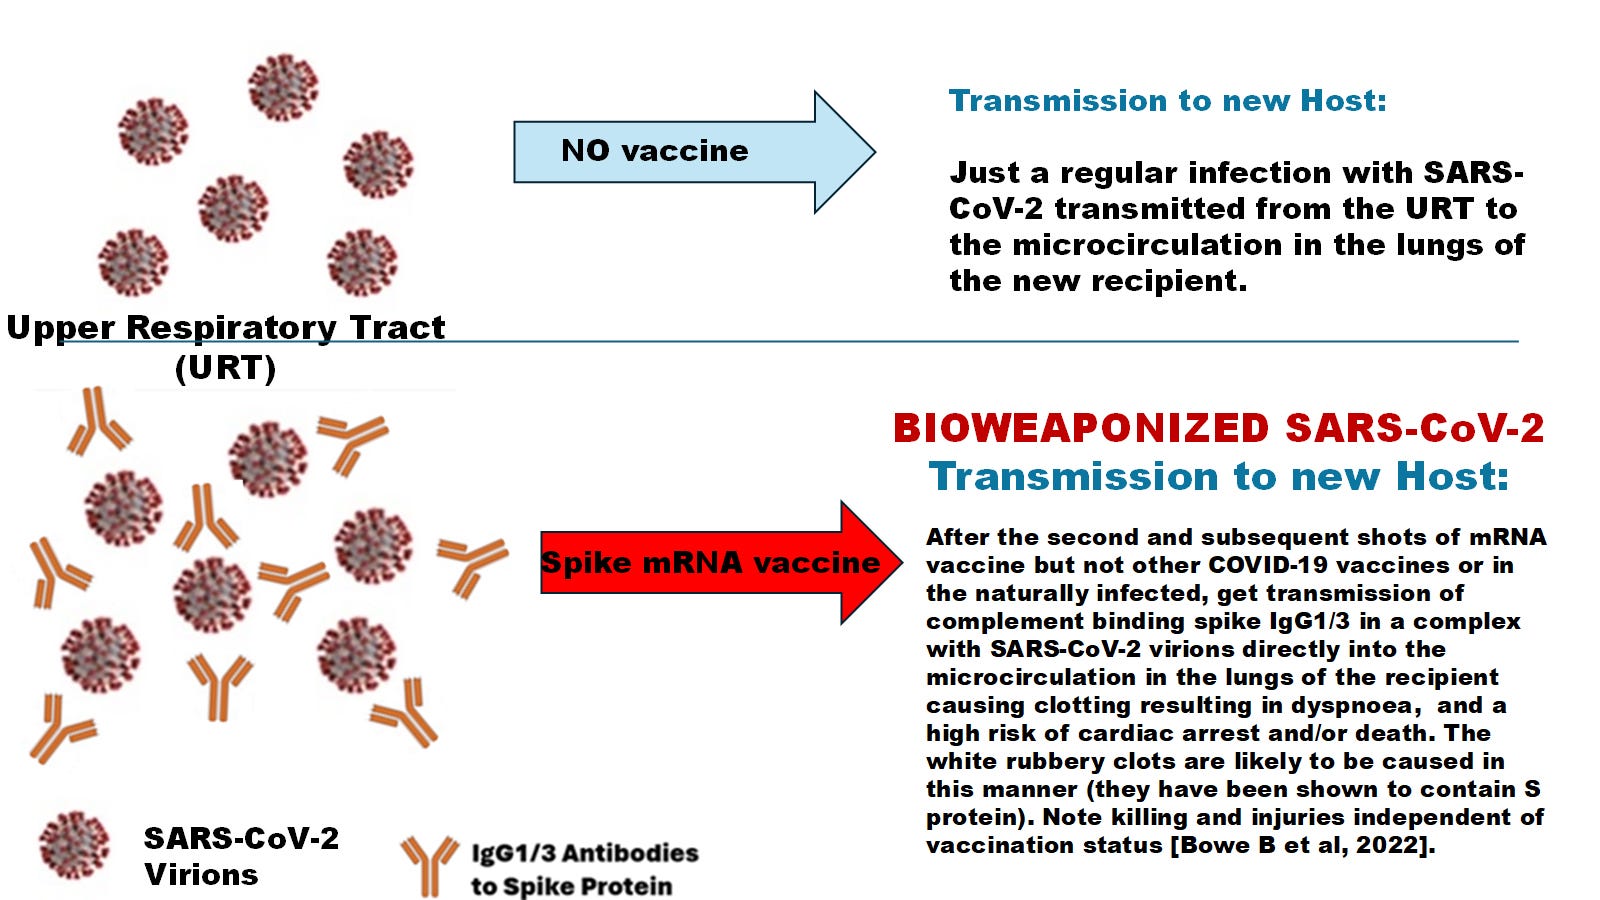
Image 6. Bioweaponized SARS-CoV-2 is More Deadly and kills regardless of vaccination status (see Images 7 and 8).
Dr. B Bowe et al [10] described the increased morbidity and mortality of an exposure to SARS-CoV-2 after about one year after the vaccination (ie., breaththrough infections) and/or in those not vaccinated who became reinfected. They did not recognize these clotting or cardiovascular insults as bioweaponized SARS-CoV-2.
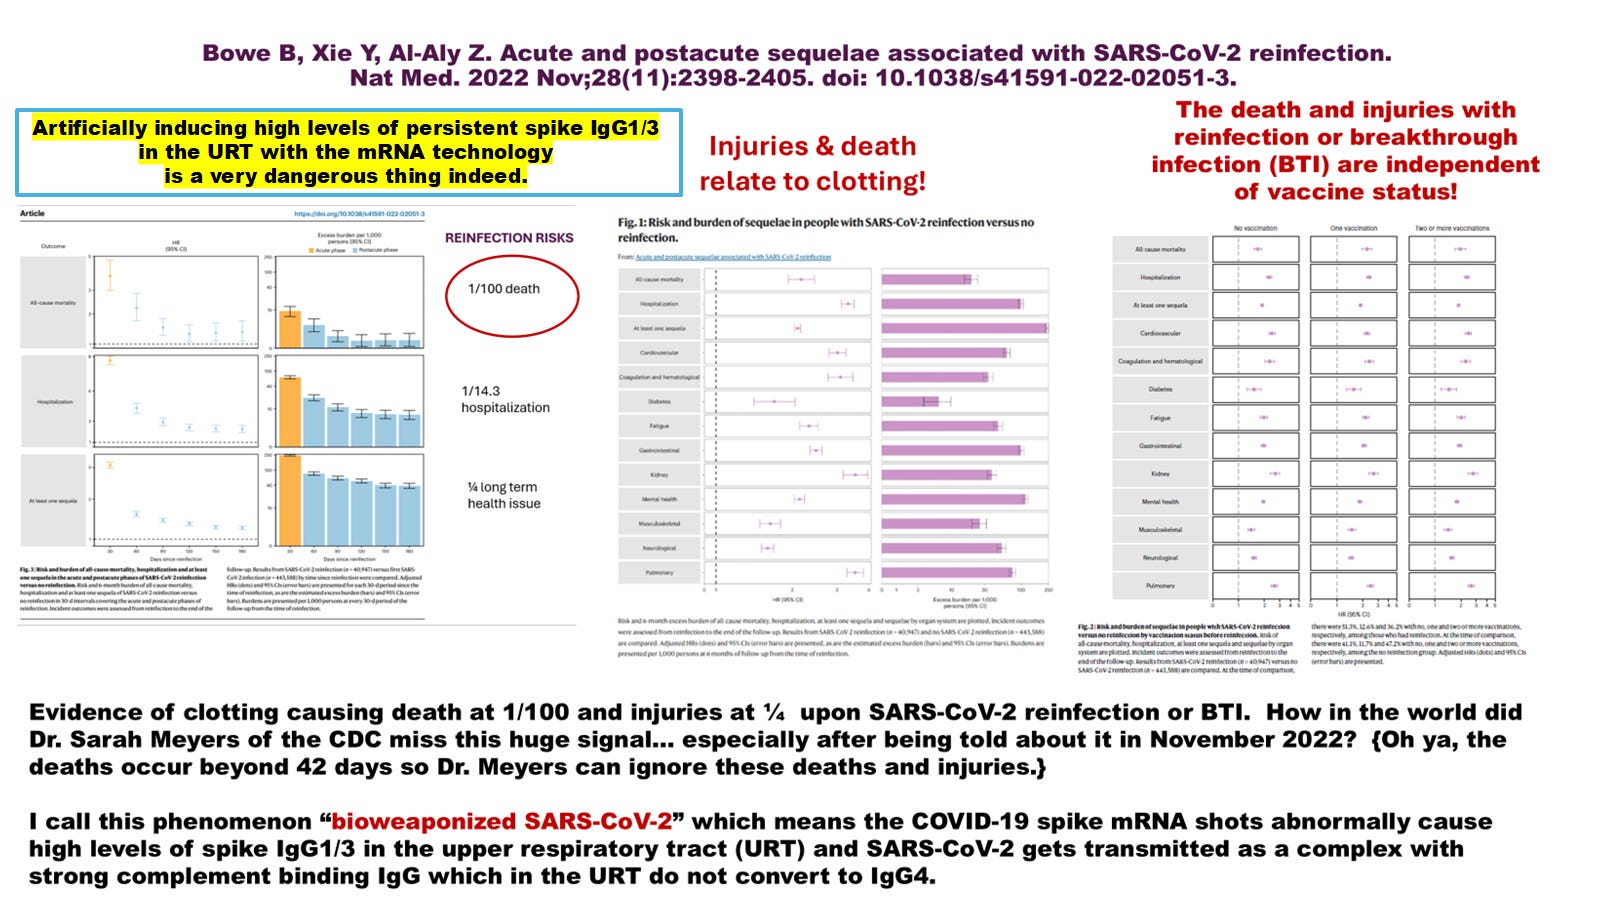
Image 7.
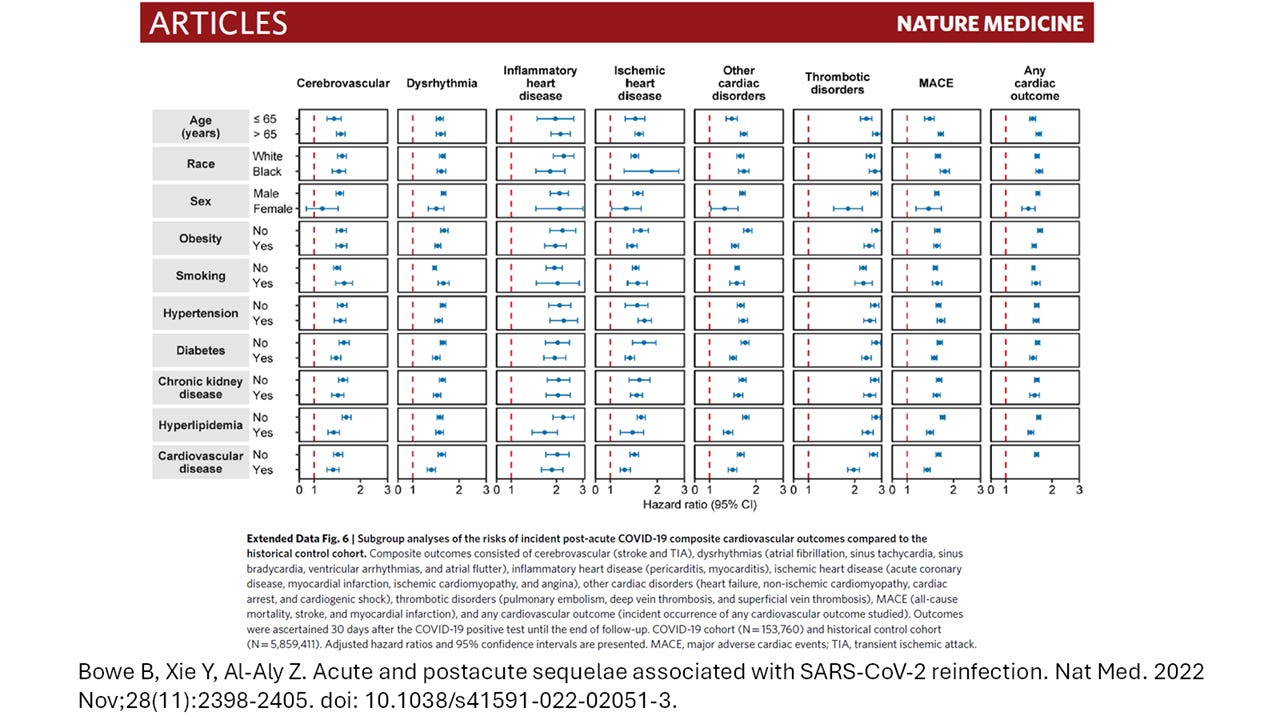
Image 8.
Since HERV-K102 by shedding from the URT generates herd immunity in part by activating the type I interferon response and likely also induces HERV-K102 trained immunity in 3rd parties (ie., induces inflammation) the evidence in Image 9 also from VAERS, seems to implicate shedding likely contributed to most myocarditis injuries. About 1/3 of the shedding cases occurred on day 0-2 which is considered pathognomonic for shedding since no spike protein can be detected in blood until after day 2 after inoculation with the spike mRNA shots.
This brings up the question of the evidence insinuating only the Pfizer-BioNTech shots contained (variable) levels of spike protein.
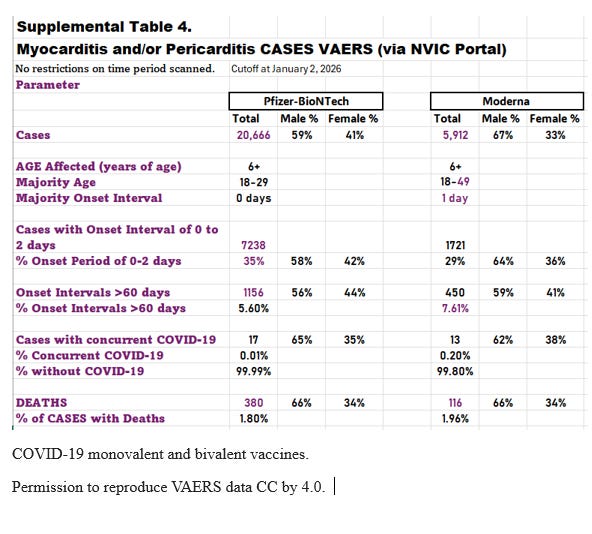
Image 9. The Myocarditis Injury Signal in VAERS might relate to Shedding.
Injuries within the first 2 days would be pathognomonic for shedding such as by the vaccinator (as generally spike protein produced by the LNPs is not detected in the blood until after 2 days. See Image 10 [11]).
Only Pfizer-BioNTech but not Moderna LNPs stimulates macrophages to produce CXCL8 in macrophages [12].
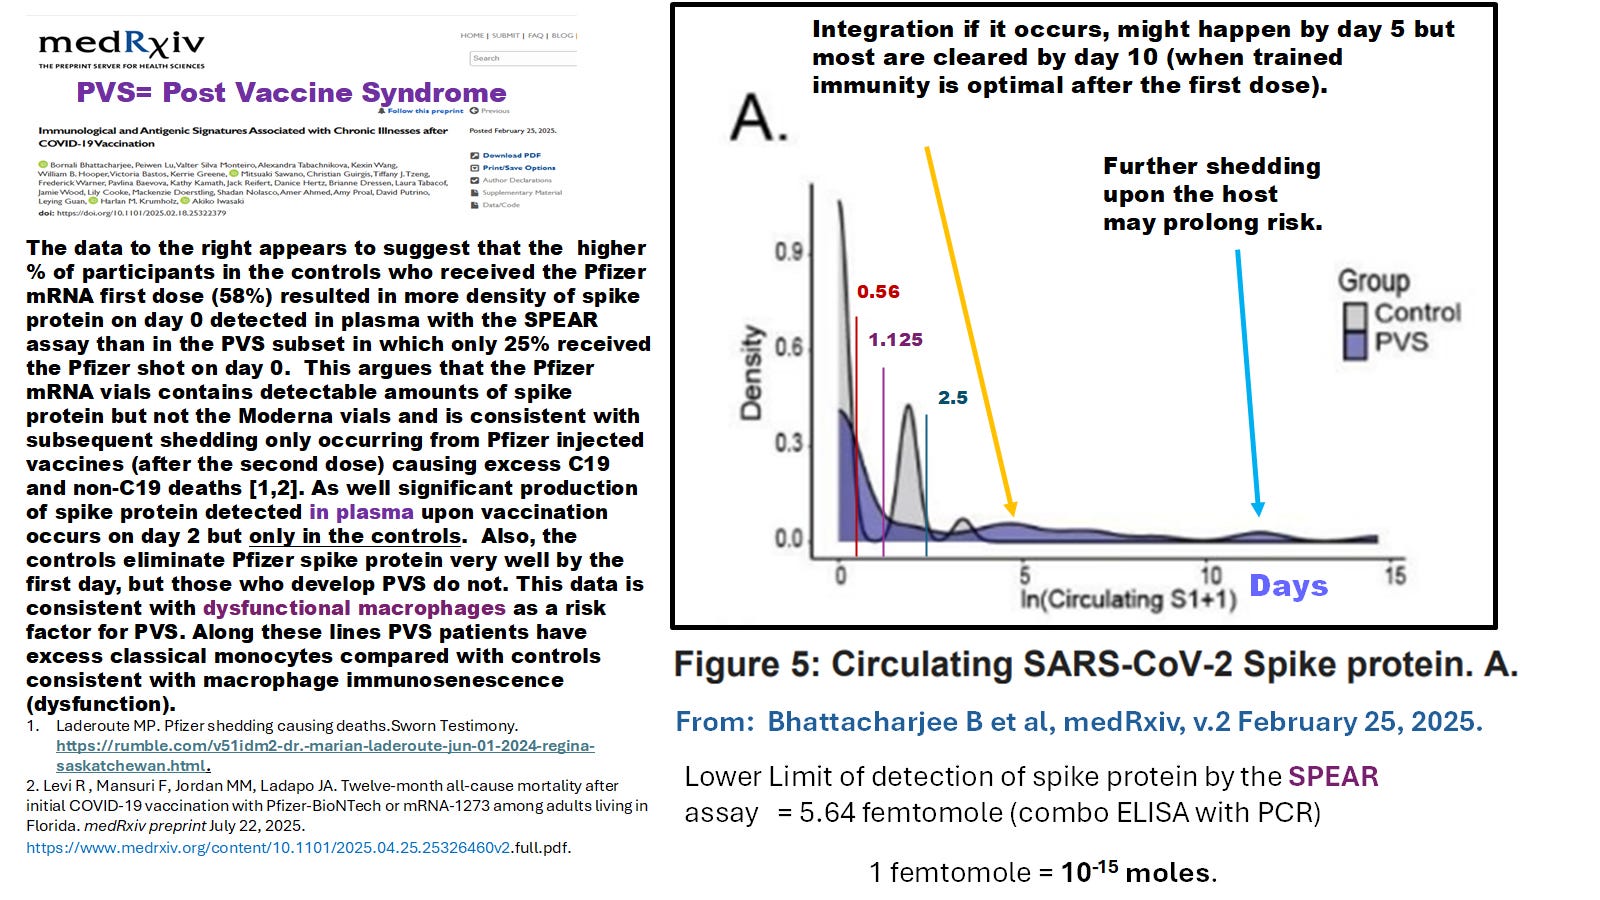
Image 10.
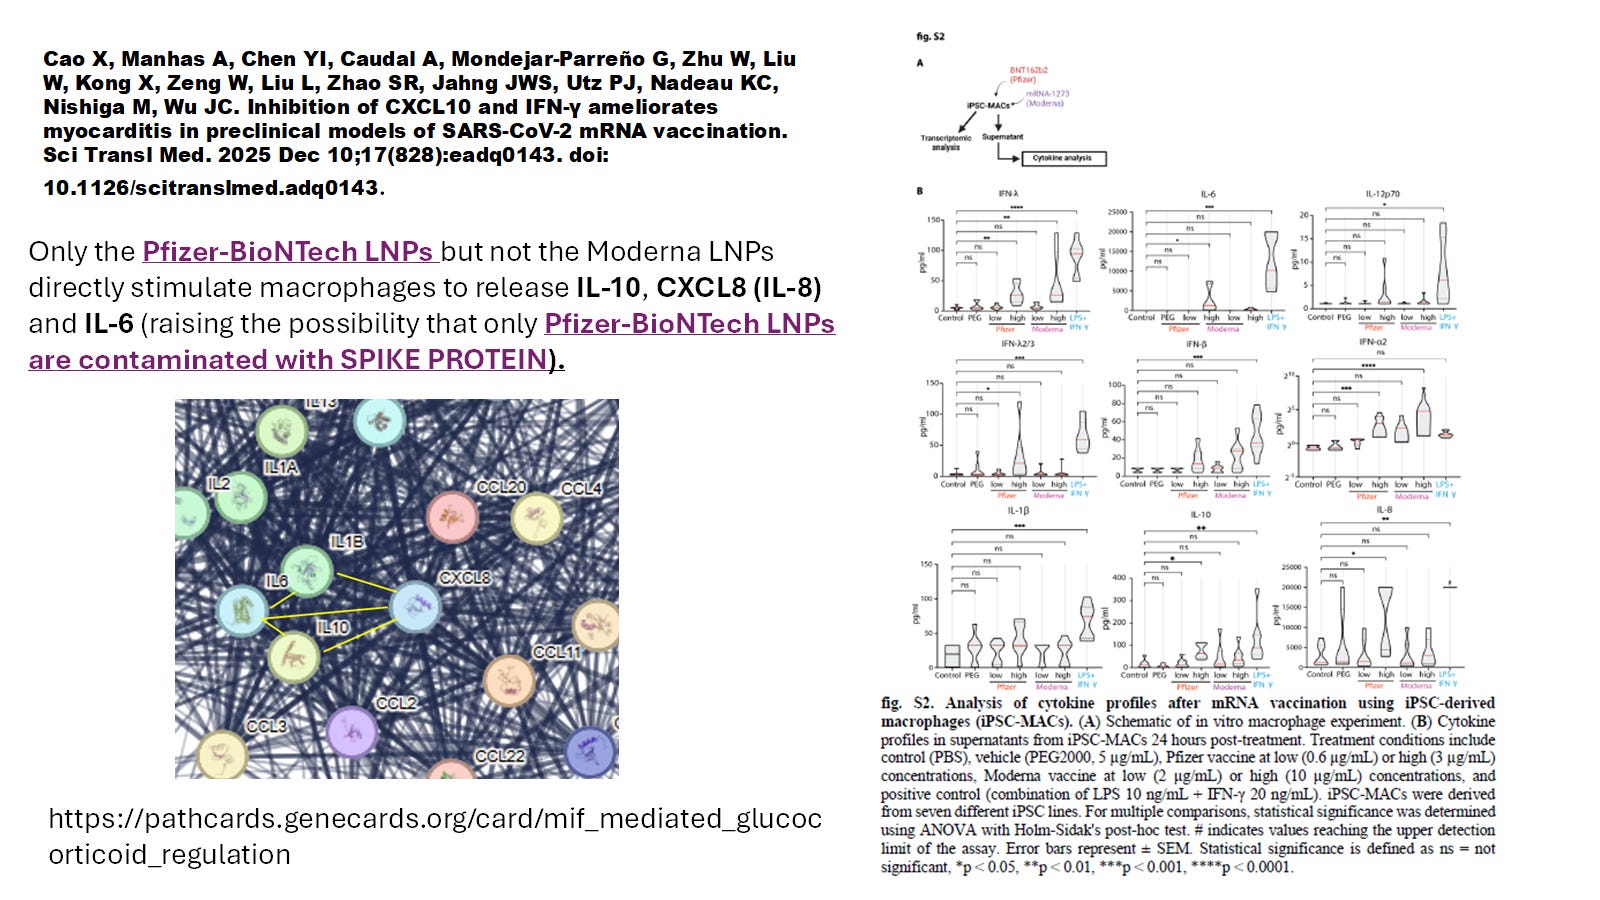
Image 11. Only the Pfizer-BioNTech LNPs but not the Moderna LNPs stimulate macrophages to produce IL-6, IL-8 (CXCL8) and IL-10 [12] Where CXCL8 induction is considered evidence of the pathogenesis of spike protein (implying spike protein is only present in the Pfizer-BioNTech LNPs).
Conclusion
So in conclusion, these new papers are consistent with the notion that the risk of integration (ie., host genetic modification incorporating spike or SV40 oncogenic/pathological sequences) is now considered real and exploits the integration machinery of the protector foamy retrovirus HERV-K102. This means that shedding which has also been implicated in myocarditis injuries, may exhibit an increased risk of 3rd party host genetic modification over mRNA LNP innoculation, but which fortunately remains relatively rare.
To reduce the risks of genetic modification, all mRNA shots should be banned from the global market including clinical trials in animals and humans.
REFERENCES
Laderoute MP. Shedding of Spike mRNA “Gene Therapy Products”: Potential Mechanisms and Mortality Outcomes. Sworn Expert Testimony to the National Citizens Inquiry, June 1, 2024.
https://rumble.com/v51idm2-dr.-marian-laderoute-jun-01-2024-regina-saskatchewan.html
Bansal S, Perincheri S, Fleming T, et al. Cutting edge: circulating exosomes with COVID spike protein are induced by BNT162b2 (Pfizer-BioNTech) vaccination prior to development of antibodies: a novel mechanism for immune activation by mRNA vaccines. J Immunol. 2021 Nov 15;207(10):2405-2410. doi: 10.4049/jimmunol.2100637.
Hulscher N, Schmidt V, Mörz M, Rogers C, von Ranke V, Zhang W, Catanzaro JA, & McCullough PA. Unprecedented persistence of vaccine mRNA, plasmid DNA, spike protein, and genomic dysregulation over 3.5 years post-COVID-19 mRNA vaccination. Zenodo. 2026 February 2. https://doi.org/10.5281/zenodo.18460099
Catanzaro JA, Hulscher N, McCullough PA. Genomic integration and molecular dysregulation in aggressive stage IV bladder cancer following COVID-19 mRNA vaccination. International Journal of Innovative Research in Medical Sciences. October 5, 2025. 10:10,380-386. http://doi.org/10.23958/ijirms/vol10-i10/2130.
Laderoute MP. Chapter 17. Controversies Concerning the Immunology of the COVID-19 Adaptive Immunity Vaccines. In: Controversies in the Pandemic. Ed(s); J Varon, PE Marik, M Rendell, J Iglesias, C de Souza, P Prabhudesai. Jaypee Brothers Medical Publishers Ltd, New Delhi, India, 2024, pp 760. ISBN: 978-93-5696-730-4.
Laderoute MP, Giulivi A, Larocque L, et al. The replicative activity of human endogenous retrovirus K102 (HERV-K102) with HIV viremia. AIDS. 2007 Nov 30;21(18):2417-24.
Laderoute MP, Larocque LJ, Giulivi A, Diaz-Mitoma F. Further evidence that human endogenous retrovirus K102 is a replication competent foamy virus that may antagonize HIV-1 replication. Open AIDS J. 2015 Dec 7;9:112-22. doi: 10.2174/1874613601509010112.
Laderoute, MP. Trained Immunity (TI) of M1-Like Foamy Macrophages: Key Role of HERV-K102 Particles. Global Translational Medicine (Accepted for publication February 9, 2026).
Laderoute MP. The Catastrophic HARM of Spike Specific IgG1/3 Antibodies in the Upper Respiratory Tract (URT) by the COVID-19 Spike mRNA GENE THERAPY Products (and how this led to widespread injuries and deaths in CHILDREN AND HEALTHY ADULTS). November 7, 2025, Brandon Manitoba
https://nationalcitizensinquiry.ca/live/#1750382268006-f73b3d3c-41ce around 4:58 to 6:01.
Bowe B, Xie Y, Al-Aly Z. Acute and postacute sequelae associated with SARS-CoV-2 reinfection. Nat Med. 2022 Nov;28(11):2398-2405. doi: 10.1038/s41591-022-02051-3.
Bhattacharjee B, Lu P, Monteiro S, et al, Immunological and Antigenic Signatures Associated with Chronic Illnesses after COVID-19 Vaccination. medRxiv, V. 2. Feb 25, 2025.
Cao X, Manhas A, Chen YI, Caudal A, Mondejar-Parreño G, Zhu W, Liu W, Kong X, Zeng W, Liu L, Zhao SR, Jahng JWS, Utz PJ, Nadeau KC, Nishiga M, Wu JC. Inhibition of CXCL10 and IFN-γ ameliorates myocarditis in preclinical models of SARS-CoV-2 mRNA vaccination. Sci Transl Med. 2025 Dec 10;17(828):eadq0143. doi: 10.1126/scitranslmed.adq0143.
Thank You, Dr. Laderoute. I will include this in the blog post I am putting together.
Most of my cleaning clients received the Pfizer BioNTech shots. I’ve seen their shot cards! I have CIRS and am sensitive to biotoxins. I was so sick several times over 2025. So far for 2026, I have been relatively healthy despite having the same vaxxed clients.